Umbilical-cord MSCs may act through insulin resistance and immune modulation — moving type 2 diabetes care from passive glucose control towards active intervention.
Umbilical-cord mesenchymal stem-cell (MSC) therapy for type 2 diabetes acts through improved insulin resistance and immune modulation. It may improve glycaemic control and delay complications. The cell source does not involve embryos, with a stronger ethical and safety profile than embryo-derived approaches.
Type 2 diabetes is a common chronic metabolic disease. Its core pathology is injury to pancreatic β-cell function or insulin resistance. Poor long-term glucose control readily leads to retinopathy, nephropathy, neuropathy and other serious complications, harming quality of life and health.
Traditional care relies mainly on diet, exercise and exogenous glucose-lowering drugs (or insulin). These can temporarily control glucose and slow progression, but cannot repair damaged islet function at the root — essentially “passive glucose control”.
Umbilical-cord MSC therapy is positioned to break that limit: activating the body’s own cellular repair for “active intervention” on the cause.
The technology centres on MSC multilineage differentiation, immunomodulation and paracrine effects, targeting core pathological links as follows:
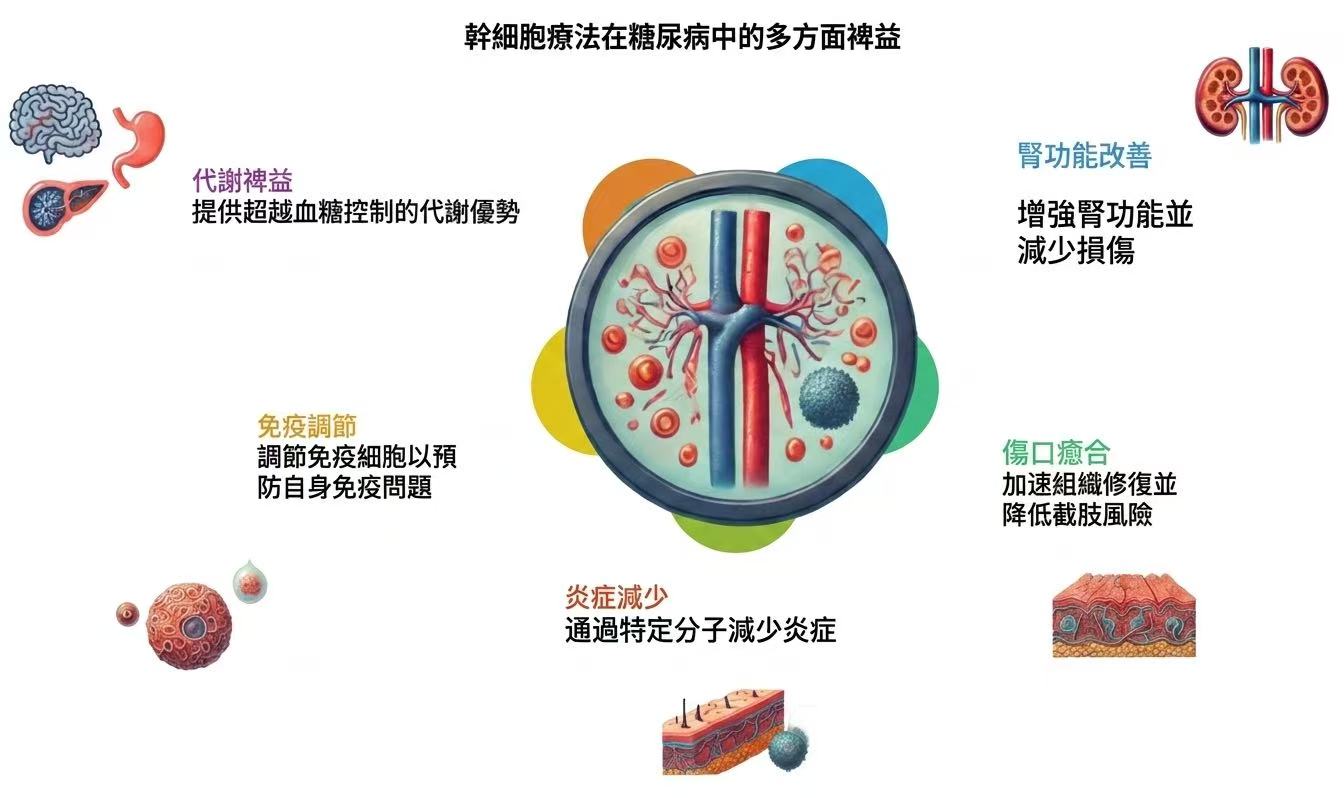
β-cell repair and regeneration
Directed differentiation: activating transcription factors such as PDX-1 and Ngn3 to become β-like cells, with glucose-stimulated insulin secretion at 78%–92% of native β cells; inducing endogenous α-to-β transdifferentiation.
Protecting survival: secreting HGF, EGF and others to inhibit β-cell apoptosis; exosomes carrying miR-375 and similar molecules that suppress apoptotic genes such as Bax, raising survival.
Improving insulin resistance and metabolic homeostasis
Raising insulin sensitivity: via the AMPK/PI3K pathway, promoting GLUT4 translocation and glucose uptake; down-regulating genes such as PEPCK, cutting hepatic glucose output.
Regulating fat metabolism: shifting adipose-tissue macrophages towards an anti-inflammatory phenotype, lowering TNF-α and other inflammatory factors, easing insulin resistance.
Complication prevention and paracrine effects
Repairing the microenvironment: secreting VEGF and others to promote angiogenesis and ease islet hypoxia; exosomes anti-fibrotic and anti-inflammatory, protecting the kidney and lowering diabetic-nephropathy risk.
Paracrine core: remote regulation of metabolism and immunity via exosomes and cytokines; stem cells homing to the pancreas for repair — the main source of efficacy.
This direction fills a gap in “root-cause treatment” of type 2 diabetes, going beyond drugs that only control glucose and cannot repair islets, and pushing care from “passive glucose control” towards a combined approach of early screening, immune intervention, cell repair and precise nutritional support.

Mature use still requires standardisation of cell preparation, quality control and efficacy evaluation, so the same chain can be copied for other metabolic diseases.
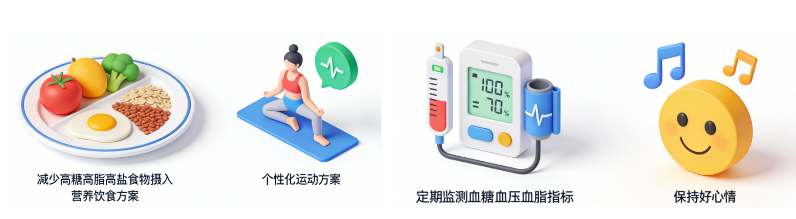
Diabetes health management: stem-cell technology does not replace conventional health management. For people with type 2 diabetes, scientific self-management remains the basis for control. Because individuals differ, daily care still needs a diet (less high-sugar, high-fat, high-salt food), a personalised exercise plan, and regular monitoring of glucose, blood pressure and lipids. Combining health management with standard treatment is what delays progression and lowers complication risk more effectively.
A proper care pathway: before treatment, a qualified clinician must assess fully and strictly exclude contraindications such as tumour and severe infection; after treatment, long-term follow-up is required, with close monitoring of body markers, to keep treatment safe.
Beware false claims: any organisation or individual claiming stem-cell therapy “cures all diseases”, is “absolutely safe” or “works in one injection” is false advertising. Patients should stay alert.
Medical disclaimer: This article is for general educational reference on longevity medicine, life science and genetic technology only. It does not constitute any diagnosis, treatment or medical advice. These fields are evolving rapidly; the content is compiled from publicly available educational material for information only and does not represent a commitment to any treatment, technology or outcome. Individual circumstances vary; actual treatments, results and potential risks may differ. Please consult a qualified clinician and follow their professional assessment and recommendations.
